How Time-Zone-Based Radiologist Scheduling Cuts Turnaround Time
Workforce data shows radiologists leaving at twice the prior rate. Here is how time-zone-based radiologist scheduling and case routing cut turnaround time.
By Trisha Seal — September 17, 2026. Trisha writes on radiology operations for RAD365, which builds the Radiology Workflow Manager — an n-tier web-based system for scheduling, case routing and reporting workflow. This article covers workflow orchestration only; RAD365 does not read or interpret studies.
Most departments treat radiologist scheduling as a rostering chore — a spreadsheet, a rotation, a few late-night swaps. The workforce data published over the last year suggests it deserves better attention than that. The pool of available readers is shrinking, the practices employing them are consolidating and spreading out, and the market for distributed reading is growing faster than almost anything else in imaging. Against that backdrop, when a radiologist is genuinely available becomes one of the strongest levers a department has over turnaround time.
The Numbers Behind the Pressure
Start with attrition. The Harvey L. Neiman Health Policy Institute, writing in the 2026 ACR Bulletin workforce update, reports that radiologists are leaving practice entirely at over twice the rate they were less than ten years ago. That is not a gentle demographic drift; it is a step change in how quickly capacity leaves the system.
Subspecialty depth is thinning in places too. The same Neiman Institute work shows pediatric radiologist headcount falling from 2,190 to 2,032 between 2016 and 2023, dropping from 6.4% of all radiologists to 4.6%. When a subspecialty is under five percent of the workforce, the probability that the right reader is available at 3 a.m. in any single facility is low by arithmetic alone.
Meanwhile the structure of practice has changed. Neiman Institute data puts average radiologists per practice at 17.9 in 2023, up from 9.7 in 2014 — an 85% increase driven by consolidation. Larger groups have, in principle, the raw coverage a small group never could. Whether they realize it depends on whether their scheduling can treat geographically dispersed radiologists as one pool.
The Market Is Already Moving This Way
Grand View Research values the global teleradiology market at $19.2 billion in 2025, projects $23.9 billion in 2026, and forecasts a 26.6% CAGR from 2026 to 2033 that would take it to $124.8 billion by 2033, with North America holding 38.3% of revenue in 2025. Read alongside the workforce figures, the story is consistent: reading capacity is being redistributed geographically because it can no longer be assembled locally in every market.
Distributing work across geography only helps if the operational layer underneath it knows who is working where, and when. That is the part that tends to be underbuilt.
Why the Roster Model Breaks Down
A conventional on-call rotation encodes responsibility, not availability. It says who is accountable for a block of hours; it does not know whether that person is mid-shift, at the end of a long day, or nine time zones away. Cases queue behind a named individual, and the queue is invisible until someone asks why the morning list is already three hours behind.
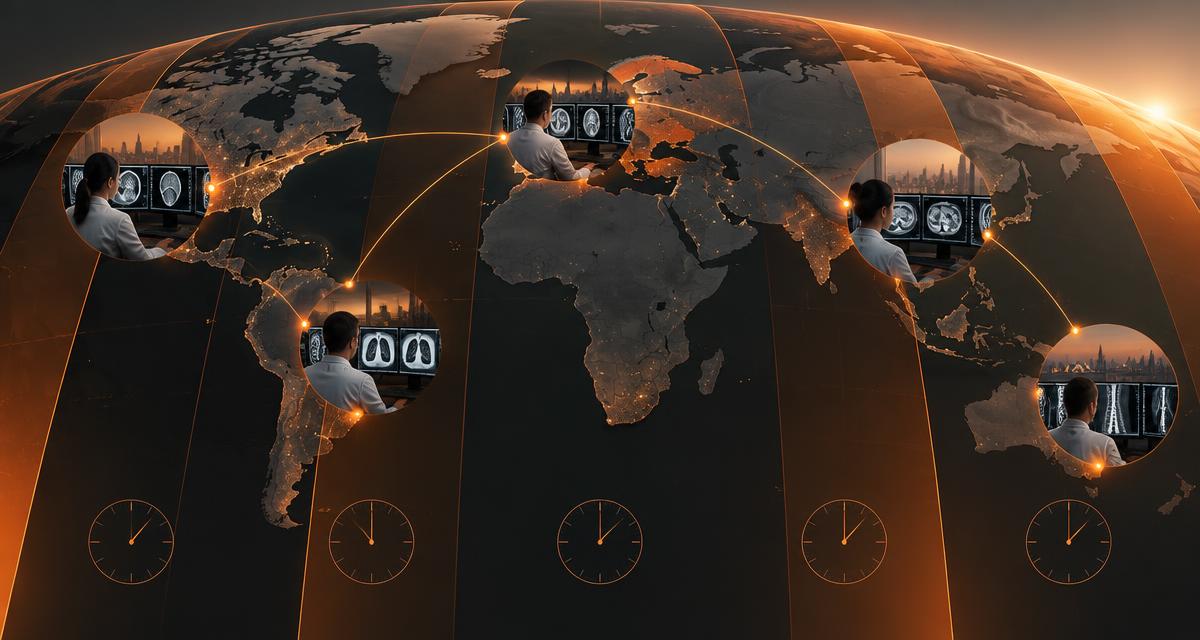
The alternative is to make availability the primary fact the system holds. RAD365's Radiology Workflow Manager records radiologist availability on a time-zone basis, so the system knows who is genuinely on shift at the moment a case arrives rather than who is nominally assigned to it.
How the Mechanism Actually Works, Step by Step
- Availability is captured in local time. Time-zone based availability scheduling establishes the working pool at any given moment across every location a group operates in.
- The case is characterized. Assignment uses modality, procedure and body part, so routing reflects what the study actually requires.
- The two filters intersect. The case goes to a radiologist who is both on shift and appropriate for the study — not one or the other.
- Reading happens without a separate PACS login. Radiologists get an interface for viewing images and reporting without needing separate PACS access, which matters when they are working outside the institution's own network. The workflow layer coordinates the case; the interpretation itself remains entirely the radiologist's.
- Handover is a controlled action. Cases can be transferred between radiologists inside the platform, with status and history intact, so a shift boundary does not become an information gap.
What the Two Models Look Like Side by Side
| Dimension | Traditional on-call rotation | Time-zone-based scheduling |
|---|---|---|
| Primary fact held | Who is responsible for these hours | Who is genuinely working right now |
| Overnight coverage | One person, often after a full day | Radiologists whose normal daytime overlaps your night |
| Case assignment | Manual, to the person on call | Filtered by modality, procedure and body part |
| Handover | Informal, outside the system | Case transfer inside the platform, history intact |
| Weekend backlog | Accumulates, lands on Monday | Capacity matched more evenly to arrival |
The Measured Effect
RAD365 reports the following results for organizations operating the Radiology Workflow Manager:
Faster turnaround time
More radiologist productivity
Less admin time
SLA compliance
How much of that a given department captures depends on where its delay currently sits. If cases are waiting for an available reader, scheduling is the binding constraint and the gain is large. If the bottleneck is upstream in acquisition or downstream in distribution, the workflow layer helps less — which is worth establishing before anyone changes a system.
Deployment and the Systems Underneath
The Radiology Workflow Manager is an n-tier web-based system that can be deployed in the cloud or on an institution's own intranet, so a distributed group can share one view of the schedule regardless of where individual radiologists sit. It works alongside the imaging estate rather than replacing it, which is why the health of that estate matters: a scheduling layer cannot compensate for an archive that is slow to serve priors, and keeping that layer stable is the job of a structured PACS support framework and ongoing managed PACS operations.
For groups running a formal quality program alongside distributed reading, peer review and QA is available as a separate optional layer. And one boundary is worth restating: RAD365 does not read, interpret or dictate studies. RWM orchestrates the workflow around the case — scheduling, routing, transfer, accounting and analytics — while clinical interpretation stays with the radiologists.
See Where Your Turnaround Time Is Actually Going
Bring your current rotation, your radiologists' locations and your turnaround targets, and we will show you what time-zone-aware scheduling and case routing would change.
Explore the Radiology Workflow Manager →Frequently Asked Questions
The Shortage Behind the Scheduling Problem
Why is radiologist scheduling becoming harder for hospitals and imaging groups?
Because the supply side is moving in the wrong direction while imaging volume is not. The Harvey L. Neiman Health Policy Institute reported in the 2026 ACR Bulletin workforce update that radiologists are now leaving practice entirely at over twice the rate they were less than ten years ago. When the pool of available readers shrinks, every hour of the week has to be covered by fewer people, and the scheduling problem stops being clerical and becomes structural.
How fast is the radiologist workforce shrinking relative to demand?
The attrition figure is the clearest signal: exits from practice have more than doubled in under a decade according to the Neiman Institute's 2026 workforce update. Meanwhile the market for distributed reading is expanding rapidly — Grand View Research values the global teleradiology market at $19.2 billion in 2025, rising to a projected $23.9 billion in 2026. Demand is being redistributed geographically because it cannot be met locally everywhere.
Why are subspecialty radiologists especially hard to schedule around?
Subspecialty pools are small to begin with and they are getting smaller in places. Neiman Institute data shows pediatric radiologist headcount fell from 2,190 to 2,032 between 2016 and 2023, dropping from 6.4% to 4.6% of all radiologists. When a subspecialty represents a few percent of the workforce, matching a case to the right reader at the right hour requires the schedule to know exactly who is genuinely available, not just who is nominally on the roster.
How has radiology practice consolidation changed staffing patterns?
It has made practices larger and more geographically spread. The Neiman Institute reports average radiologists per practice grew from 9.7 to 17.9 between 2014 and 2023, an 85% increase. A bigger practice can in principle cover more hours, but only if its scheduling system can treat radiologists in different locations and time zones as one coordinated pool rather than several separate rosters.
How Time-Zone-Based Scheduling Works
What does time-zone-based radiologist scheduling actually mean?
It means availability is recorded and interpreted in each radiologist's own local time, so the system knows who is genuinely on shift at any given moment rather than who appears on a roster written in one head-office time zone. In RAD365's Radiology Workflow Manager this is handled as time-zone based availability scheduling, and it is the foundation everything else in the routing logic sits on.
How is it different from a traditional on-call rotation?
An on-call rotation assigns a named person to a block of hours and relies on them being reachable. Time-zone-based scheduling assigns work to whoever is actually within their working window, which is a different question. The rotation model asks who is responsible; the time-zone model asks who is awake, working and qualified right now.
Does it require radiologists to work unusual hours?
The point is usually the opposite. By drawing on radiologists whose ordinary daytime hours overlap another site's night, a distributed schedule can cover overnight periods without asking anyone to work against their own body clock. Whether that is available depends entirely on the composition of the group; the scheduling model simply makes it possible to use the spread a group already has.
How does modality- and body-part-based case routing work alongside time-zone scheduling?
They operate as two filters on the same decision. Availability scheduling narrows the pool to radiologists who are genuinely on shift; case assignment then narrows further based on modality, procedure and body part, so the case reaches someone both available and appropriate. Either filter alone produces the familiar failure modes — a qualified reader who is asleep, or an available reader who is not the right fit for the study.
Can a radiologist transfer a case to a colleague in a different time zone?
Yes. Cases can be transferred between radiologists inside the Radiology Workflow Manager, which is what makes handover at the edge of a shift a controlled action rather than an email and a hope. The case, its status and its history move together, so nothing has to be reconstructed by the receiving radiologist.
The Turnaround Time Impact
How much can turnaround time improve with distributed, time-zone-aware scheduling?
RAD365 reports 40-60% faster turnaround time for organizations running the Radiology Workflow Manager, alongside 25-35% more radiologist productivity, 90% less admin time and 100% SLA compliance. The size of the gain in any individual department depends on how much of its current delay comes from cases waiting for an available reader rather than from the reading itself.
Why does turnaround time usually suffer overnight and on weekends without distributed coverage?
Because the queue keeps filling while the reading capacity drops to one person or none. Cases accumulate through the night and land on the morning shift as a backlog that has to be worked through on top of that day's normal volume. Distributed coverage flattens the curve by matching capacity to arrival more evenly across the full week.
Is the teleradiology and distributed-reading market actually growing?
Substantially. Grand View Research values the global teleradiology market at $19.2 billion in 2025 and projects $23.9 billion in 2026, growing at a 26.6% CAGR from 2026 to 2033 to reach $124.8 billion by 2033, with North America holding a 38.3% revenue share in 2025. The direction of travel is clearly toward distributed rather than purely on-site reading.
Does distributed scheduling help with radiologist burnout as well as turnaround time?
It can, though it is not a cure on its own. Reducing the number of people required to work against their own circadian rhythm, and removing the administrative friction of chasing case status, both address recognized contributors to burnout. Given that the Neiman Institute's 2026 update reports exits from practice at over twice the rate of less than a decade ago, retention pressure is a reason to take workflow design seriously rather than treat it as an efficiency nicety.
Which studies benefit most from time-zone-aware scheduling?
The ones that arrive outside conventional working hours and cannot wait for the morning list — overnight emergency department imaging, weekend inpatient work and transfer-related studies. These are also the cases where a traditional rotation is thinnest, so matching them to a radiologist whose ordinary working day is already underway somewhere else produces the largest turnaround improvement.
Making It Work Operationally
What technology does time-zone-based radiologist scheduling depend on?
It depends on a workflow layer that holds availability, case attributes and assignment logic in one place and is reachable from anywhere the radiologists are. RAD365's Radiology Workflow Manager is an n-tier web-based system deployable in the cloud or on an institution's own intranet, which is what allows a distributed group to work from a single shared view of the schedule.
Do radiologists need separate PACS access to work across a distributed scheduling model?
Not within the Radiology Workflow Manager. Radiologists get an interface for viewing images and reporting without needing separate PACS access, which removes a practical obstacle for anyone working outside the main institutional network. Note that RWM orchestrates the workflow around the case; the interpretation itself remains entirely the radiologist's work.
How does billing and accounting stay accurate when radiologists work across time zones?
By deriving it from the same workflow record rather than reconstructing it afterwards. When assignment, transfer and completion are all captured in the platform as they happen, the accounting layer reads from a single consistent history, which is where most cross-time-zone reconciliation errors come from in the first place.
Can a single workflow platform combine scheduling, case routing and reporting in one place?
That is the design intent of the Radiology Workflow Manager: availability scheduling, modality- and body-part-based routing, a reporting interface, case transfer, and the accounting and analytics layers around them all sit in the same web-based system. Consolidating them matters because the handoffs between separate tools are where turnaround time quietly leaks away.
Related Services
- Radiology Workflow Manager: scheduling, routing and reporting
- Managed PACS services and ongoing operations
- How our PACS support framework is structured
- Radiology administrative support
- Peer review and QA as an optional add-on
Sources
- Harvey L. Neiman Health Policy Institute / ACR Bulletin, 2026 radiologist shortage and workforce update — acr.org
- Grand View Research, "Teleradiology Market Size, Share, Growth Report" — grandviewresearch.com